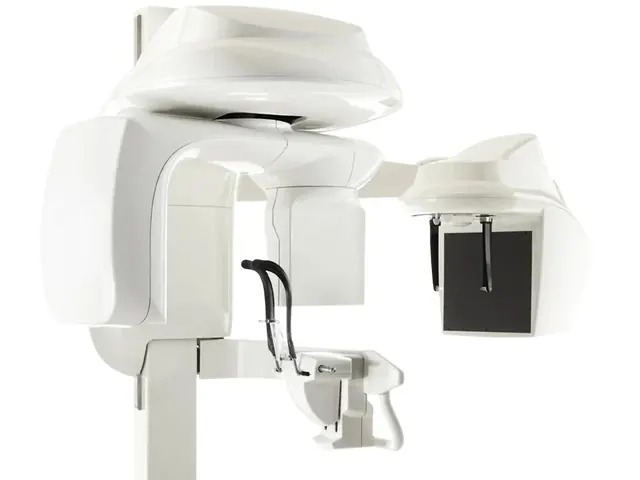
3-in-1 combination units bundle panoramic, cephalometric, and CBCT imaging modalities into a single floor-standing machine, delivering comprehensive 2D and 3D dental imaging capability from one installation. For practices commissioning imaging capability for the first time — or replacing multiple aging units with a single modern platform — the decision between 3-in-1 combination, 2-in-1 panoramic+cephalometric, and dedicated CBCT (with separate panoramic if needed) involves meaningful tradeoffs in capital cost, space efficiency, workflow integration, image quality, and long-term flexibility. This guide walks through the 3-in-1 vs. dedicated CBCT decision framework for practices sourcing imaging equipment from Shanghai.
The three architectural approaches
3-in-1 combination unit (pan + ceph + CBCT)
- Architecture: single floor-standing unit housing panoramic, cephalometric, and CBCT imaging in shared gantry with mode-switching
- Capital cost FOB Shanghai: USD 32,000–55,000 for Chinese mid-tier
- Floor space: 2.2×1.8m footprint plus ceph arm extension (approximately 3.0×1.8m total)
- Typical detector design: shared detector with mode switching, or dual detector (panoramic + CBCT with CBCT also handling ceph)
2-in-1 pan+ceph + separate CBCT (or no CBCT)
- Architecture: dedicated 2-in-1 pan+ceph unit, separate dedicated CBCT unit (or no CBCT capability)
- Capital cost FOB Shanghai: USD 18,000–32,000 for 2-in-1 pan+ceph; + USD 28,000–55,000 for separate CBCT if added
- Floor space: 2.2×1.8m for 2-in-1 (with ceph arm) + separate CBCT room if CBCT added
- Flexibility: modular expansion — add CBCT later if not initially justified
Dedicated CBCT (with optional 2D capability)
- Architecture: dedicated CBCT unit; some units offer panoramic reconstruction from CBCT (“synthetic panoramic”)
- Capital cost FOB Shanghai: USD 28,000–80,000 depending on tier
- Floor space: 2.0×1.8m typical footprint (no ceph arm extension)
- Limitation: no true lateral cephalometric; synthetic panoramic acceptable quality but not optimized
Decision framework by practice type
Orthodontic-focused practice
- Primary imaging needs: panoramic (routine), lateral cephalometric (records, planning), CBCT (selective for impactions, surgical planning)
- Optimal architecture: 3-in-1 combination provides all three modalities in unified workflow
- Rationale: orthodontic practice needs ceph capability routinely; CBCT is occasional; 3-in-1 delivers both without running separate CBCT
- Alternative: 2-in-1 pan+ceph adequate if CBCT case volume < 3–5 per month; external CBCT referral for CBCT-indicated cases
Implant-focused general practice or implant specialty
- Primary imaging needs: CBCT (primary for implant planning), panoramic (screening and overview)
- Lateral ceph: rarely needed for implant practice
- Optimal architecture: dedicated CBCT + separate panoramic unit, or 3-in-1 if panoramic workflow volume justifies
- Rationale: implant practice uses CBCT heavily; ceph capability unused; paying for unused capability in 3-in-1 is economic waste
- Alternative: 3-in-1 acceptable if practice does some orthodontic work or records orthodontic referrals internally
Endodontic specialty practice
- Primary imaging needs: small-FOV CBCT (primary), intraoral radiograph (routine)
- Lateral ceph: not needed
- Panoramic: occasional
- Optimal architecture: dedicated small-FOV CBCT; intraoral X-ray sensor for routine periapical imaging
- Rationale: endodontic practice needs high-resolution small-FOV CBCT specifically; 3-in-1 optimizes for large-FOV general imaging not endodontic specialty needs
Comprehensive multi-disciplinary practice
- Primary imaging needs: all modalities (panoramic, cephalometric, CBCT, intraoral)
- Optimal architecture: 3-in-1 combination unit for comprehensive capability in unified workflow
- Rationale: mixed orthodontic + restorative + implant + endodontic case mix uses all imaging modalities regularly; 3-in-1 integration justifies capability premium
- Budget consideration: 3-in-1 is typically more cost-effective than separate pan+ceph + separate CBCT for comprehensive practice
Orthognathic surgical practice
- Primary imaging needs: large-FOV CBCT (primary for surgical planning), lateral cephalometric (routine), panoramic (routine)
- Optimal architecture: 3-in-1 or premium dedicated CBCT with ceph capability
- Rationale: orthognathic workflow uses CBCT + ceph together extensively; 3-in-1 provides efficient workflow
Oral surgery practice (implant + extraction + pathology focus)
- Primary imaging needs: CBCT (primary for surgical planning), panoramic (routine)
- Lateral ceph: rarely needed unless orthognathic integrated
- Optimal architecture: dedicated CBCT + panoramic, or 3-in-1 if ceph is occasional need
Technical architecture tradeoffs
Shared detector architecture (legacy 3-in-1)
- Single flat-panel detector that repositions for different modalities
- Advantage: lower manufacturing cost
- Limitation: detector positioning mechanism adds complexity and potential failure point
- Limitation: detector size typically compromised for both panoramic and CBCT needs
- Workflow: mode switch requires detector reconfiguration (30–90 seconds)
- Quality: CBCT image quality acceptable but not optimal due to detector compromise
Dual detector architecture (modern 3-in-1)
- Dedicated panoramic detector + dedicated CBCT detector (with CBCT detector also handling cephalometric when applicable)
- Advantage: each detector optimized for its modality
- Advantage: faster mode switching (no detector reconfiguration)
- Advantage: better image quality per modality
- Cost: higher manufacturing cost (reflected in unit price)
- Standard: mid-tier and premium 3-in-1 units
Dedicated CBCT detector architecture
- Single large-area flat-panel detector optimized purely for CBCT
- Advantage: optimal CBCT image quality
- Advantage: simpler mechanical design
- Limitation: no native panoramic or cephalometric capability (synthetic panoramic only)
Image quality comparison
Panoramic image quality
- Dedicated 2D panoramic: optimized detector, 5–6.5 lp/mm resolution, best panoramic image quality
- 3-in-1 with dual detector: comparable panoramic quality to dedicated 2D
- 3-in-1 with shared detector: acceptable but typically 4–5 lp/mm panoramic resolution
- Synthetic panoramic from dedicated CBCT: derived from CBCT volume, lower resolution and geometric accuracy than true panoramic
Cephalometric image quality
- Dedicated ceph detector or 3-in-1 dual-detector: 30×25cm capture area, 4–6 lp/mm resolution
- 3-in-1 shared detector: may require stitched ceph (two captures combined), acceptable quality
- Dedicated CBCT: no lateral cephalometric capability
CBCT image quality
- Dedicated CBCT: optimal CBCT image quality, full voxel range, premium reconstruction
- 3-in-1 with dual detector: very good CBCT quality, comparable to mid-tier dedicated CBCT
- 3-in-1 with shared detector: adequate CBCT quality but detector is compromise between modalities; typically limited voxel and FOV range
Workflow efficiency comparison
Single-patient workflow (all three modalities needed)
- 3-in-1 combination: single patient positioning, sequential captures in 3–5 minutes total; no patient repositioning between modalities
- Separate pan+ceph + separate CBCT: patient moves between two rooms, separate positioning for each; 8–15 minutes total workflow
- Benefit to 3-in-1: 30–60% time saving, improved patient experience, reduced staff workflow
Single-modality workflow (most common case)
- 3-in-1: single mode selected, standard workflow
- Dedicated CBCT: single mode, optimized workflow
- No meaningful difference for single-modality appointments
Multi-patient throughput
- 3-in-1 shared detector: mode switching adds 30–90 seconds between patients using different modalities
- 3-in-1 dual detector: immediate mode switching
- Dedicated machines: no mode switching, but patient movement between rooms
Capital cost analysis
Comprehensive equipment scenario (practice needing all modalities)
Option A: 3-in-1 combination unit
- 3-in-1 unit (mid-tier): USD 40,000 FOB + USD 8,000 shipping/duty/install = USD 48,000 landed
- Imaging workstation: USD 2,500 landed
- Shielding and room: USD 8,000
- Total: USD 58,500
Option B: Separate 2-in-1 pan+ceph + dedicated CBCT
- 2-in-1 pan+ceph (mid-tier): USD 24,000 FOB + USD 5,000 landed cost = USD 29,000 landed
- Dedicated CBCT (mid-tier): USD 42,000 FOB + USD 8,000 landed cost = USD 50,000 landed
- 2× imaging workstations: USD 5,000
- 2× shielding and rooms: USD 14,000
- Total: USD 98,000
Option C: Dedicated CBCT only (no ceph capability)
- Dedicated CBCT with synthetic panoramic (mid-tier): USD 38,000 FOB + USD 7,000 landed = USD 45,000 landed
- Imaging workstation: USD 2,500
- Shielding and room: USD 8,000
- Total: USD 55,500
- Limitation: no lateral cephalometric; must refer ceph cases externally or skip ceph
Savings analysis
- 3-in-1 (Option A) vs. separate (Option B): USD 39,500 capital savings favoring 3-in-1
- 3-in-1 (Option A) vs. dedicated CBCT only (Option C): USD 3,000 premium for ceph capability
- Decision point: is lateral ceph capability worth USD 3,000 over 7–10 year equipment life?
Space efficiency
3-in-1 floor space
- Main unit: 2.2×1.8m
- Ceph arm extension: adds 0.8–1.2m lateral space
- Total: approximately 3.0×1.8m (5.4 m²)
- Shared imaging room
Separate units floor space
- 2-in-1 pan+ceph: 3.0×1.8m (5.4 m²)
- Dedicated CBCT: 2.0×1.8m (3.6 m²)
- Total: 9 m²
- Two separate imaging rooms
Space premium of separate units
- 3.6 m² additional space required
- In space-constrained practices, this is a meaningful commitment
- In large facilities, space premium may be acceptable for image quality benefits
Flexibility and future-proofing
3-in-1 flexibility
- Single unit serves all imaging needs
- Single unit failure eliminates all imaging until repair
- Upgrade requires full unit replacement
- Software upgrades shared across modalities
Separate units flexibility
- Redundancy: one unit failure leaves other modalities available
- Modular upgrade: replace individual modalities as technology evolves
- CBCT technology advances faster than 2D panoramic; separate architecture allows CBCT upgrade without replacing 2D capability
Regulatory considerations
- Classification: 3-in-1 is typically classified as Class IIb medical device (CBCT-level classification)
- Destination country registration: single registration process for 3-in-1 vs. separate registrations for separate units (generally simpler with 3-in-1)
- Radiation safety: single installation and shielding analysis for 3-in-1 vs. two separate installations
- Operator certification: single equipment training vs. multiple equipment types
Chinese 3-in-1 combination unit quality tiers
Entry-tier 3-in-1 (USD 32,000–42,000 FOB)
- Shared detector architecture
- Limited CBCT FOV (typically up to 12×9cm)
- 150µm minimum voxel typical
- Basic imaging software
- Fit: comprehensive general practice, cost-conscious commissioning
Mid-tier 3-in-1 (USD 42,000–52,000 FOB)
- Dual detector architecture
- CBCT FOV up to 16×10cm
- 100µm voxel capability
- Comprehensive software including implant planning
- Fit: mainstream comprehensive practice, orthognathic surgical practice
Premium 3-in-1 (USD 52,000–70,000 FOB)
- Dual detector with premium CMOS
- CBCT FOV up to 17×13cm, 75µm voxel capability
- Advanced reconstruction, metal artifact reduction, motion compensation
- Premium software with specialty analysis tools
- Fit: specialty practice, academic, teaching institution
Typical procurement scenarios
Scenario 1: New practice commissioning comprehensive imaging
- Mid-tier 3-in-1 combination unit: USD 45,000 FOB
- Total landed: USD 55,000–62,000
- Commissioning time: 3–5 months
- Rationale: single unit establishes comprehensive imaging capability with integrated workflow
Scenario 2: Existing practice replacing aging panoramic + adding CBCT
- 3-in-1 replacement: USD 45,000 landed total
- Alternative: keep aging panoramic, add dedicated CBCT: USD 50,000–55,000 for CBCT
- 3-in-1 typically more economical and better long-term architecture
Scenario 3: Implant-focused specialty practice with modest 2D needs
- Dedicated CBCT with synthetic panoramic: USD 42,000 landed
- Ceph capability not needed; savings justify dedicated architecture
- Primary specialty workflow optimized
Scenario 4: Orthognathic surgical practice
- Premium 3-in-1 with ortho/surgical software: USD 65,000 landed
- All modalities integrated; surgical planning software ecosystem
- Premium tier justified by specialty clinical needs
Common decision mistakes
- Buying 3-in-1 for implant-focused practice: paying for unused ceph capability; dedicated CBCT is typically better value for pure implant practice
- Buying dedicated CBCT without ceph for orthodontic practice: missing routine ceph capability creates ongoing referral workflow friction
- Buying separate units without space justification: space premium is substantial; justify with clinical workflow analysis
- Assuming 3-in-1 image quality equals dedicated units: shared-detector 3-in-1 compromises on image quality; dual-detector units approach but don’t always match dedicated quality
- Over-investing in premium 3-in-1 for general practice: mid-tier 3-in-1 is usually adequate; premium tier justifies only for specialty applications
- Under-budgeting for shielding and installation: 3-in-1 requires comprehensive radiation shielding; plan accordingly
Decision framework summary
3-in-1 combination is the right choice when
- Practice needs all three modalities (pan + ceph + CBCT) regularly
- Single imaging room available (space constraint)
- Comprehensive multi-disciplinary practice
- Orthognathic surgical focus
- Budget prioritizes breadth over specialty image quality
Dedicated CBCT is the right choice when
- Implant, endodontic, or oral surgery specialty focus
- Lateral ceph rarely needed
- Specialty clinical workflow justifies optimized CBCT image quality
- Budget prioritizes depth in primary clinical specialty
Separate 2-in-1 pan+ceph + dedicated CBCT is the right choice when
- Space available for two imaging rooms
- Clinical volume justifies dual-room workflow efficiency
- Prefer modular architecture for future upgrade flexibility
- Large multi-operatory facility with established imaging workflow
Deciding between 3-in-1 combo and dedicated CBCT from Shanghai?
WhatsApp us with your practice clinical mix (general, orthodontic, implant, endodontic, surgical), expected imaging modality volume by type (panoramic scans/month, ceph/month, CBCT/month), available imaging room space, destination country, and budget. We’ll work through the 3-in-1 vs. dedicated CBCT decision for your specific context, compare total landed cost and 5-year TCO across architectures, propose CBCT and imaging unit options matched to your clinical workflow, and quote FOB Shanghai pricing with full commissioning package landed cost analysis.
Ready to price this out?
Tell us the model, quantity and destination port. We reply with FOB or CIF pricing, current stock status and a video demo where the unit is in our Shanghai warehouse.